
Stabilize
The bite plate provides the intraoral anchor while the clinician confirms fit, comfort, jaw position, and safe use.
Built on rehabilitation principles
Evaluation, progressive loading, functional goals, continuity of care, and measurable advancement form the clinical foundation of the ISO Metrik model for participating physical therapy clinics.
ISO Metrik is intended to support skilled physical therapy—not replace examination, differential screening, or referral.
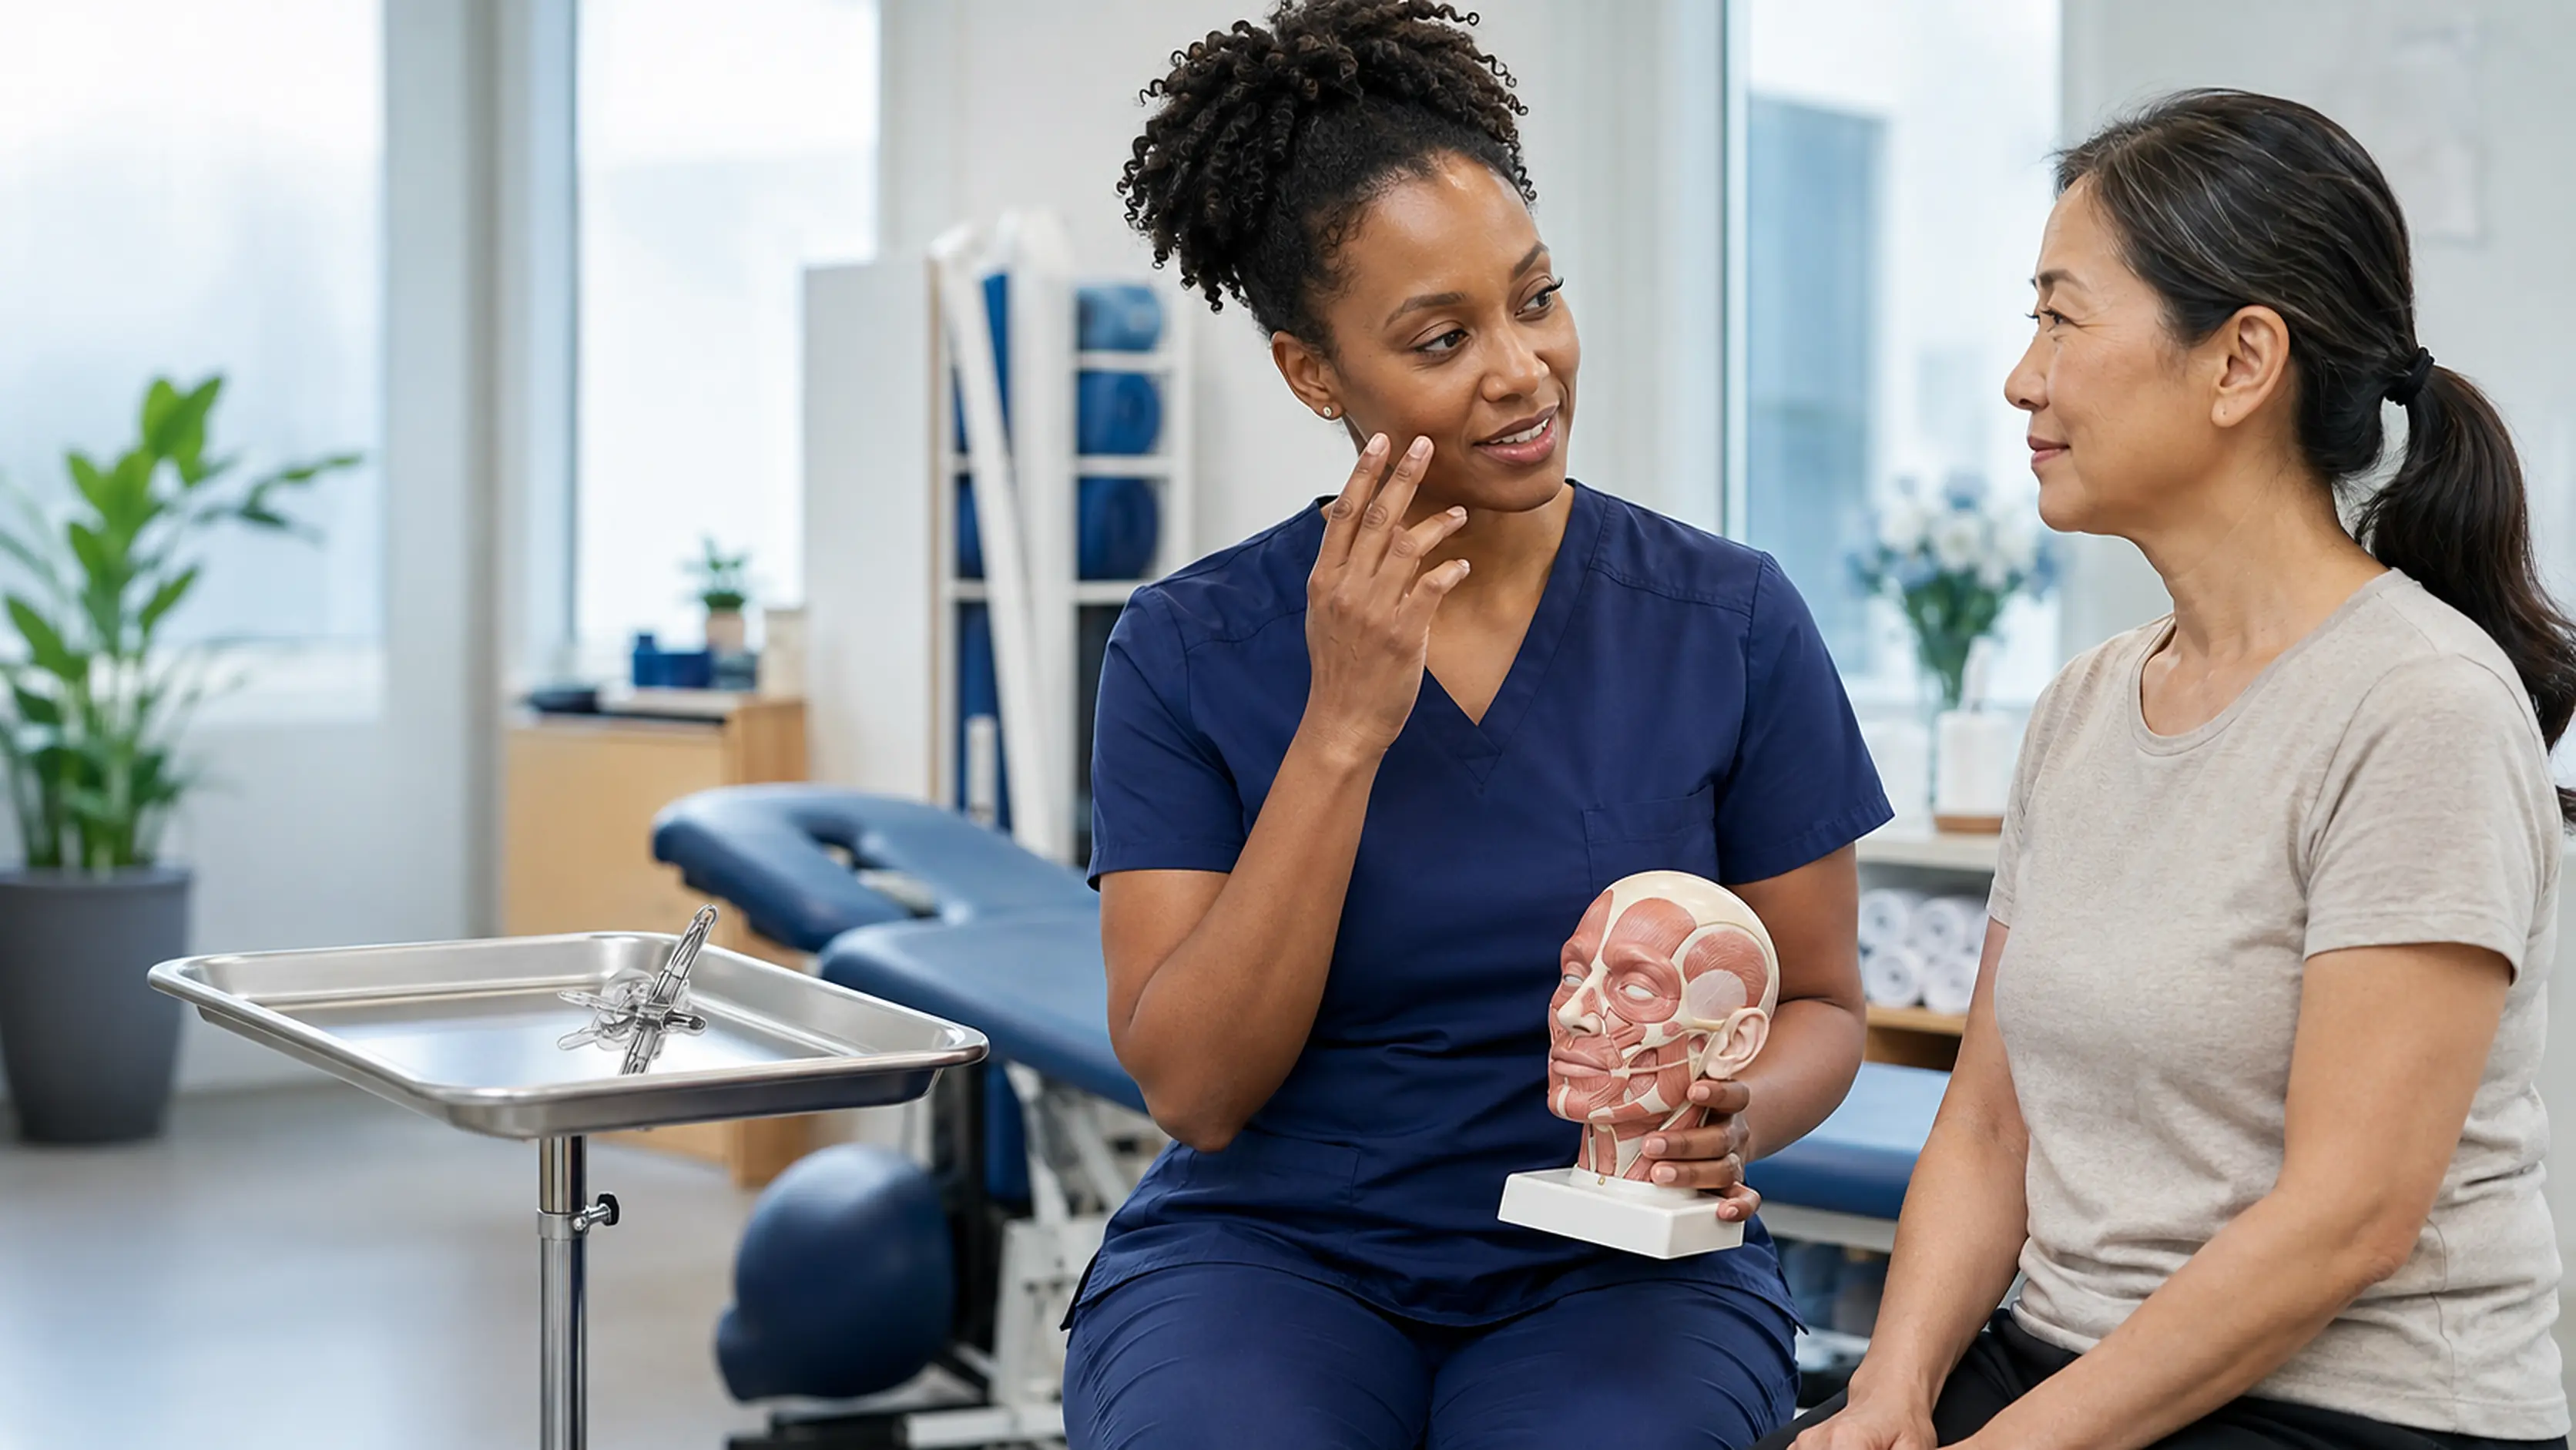
Clinical fit
ISO Metrik is intended to fit within a skilled plan of care. The physical therapist remains responsible for examination, candidacy, goal selection, dosage, progression, documentation, safety, and interdisciplinary referral.
How it works
The device combines intraoral stabilization, guided movement, lip contact, and adjustable resistance. These videos from the ISO Metrik User Manual show the device and its three primary placement orientations. A trained clinician determines whether the device is appropriate and selects the treatment parameters.
The bite plate, glide bar, lip holders, cushions, and resistance bands work as one system. The device provides a repeatable mechanical setup that can be incorporated into a provider-directed facial rehabilitation plan.
The bite plate provides the intraoral anchor while the clinician confirms fit, comfort, jaw position, and safe use.
The stainless-steel glide bar links the bite plate and lip holders and provides a controlled track and measurement reference for movement.
The lip holders provide the contact point for clinician-directed facial movement while the patient performs the selected task with controlled form.
Resistance bands provide adjustable external load. The treating clinician selects orientation, resistance, repetitions, hold time, rest, and progression based on the patient response.
Device placements
Demonstrates the horizontal device orientation and controlled movement pattern.
Demonstrates the vertical device orientation and controlled movement pattern.
Demonstrates the 45-degree right/left orientation used when a clinician selects an oblique movement direction.
Training videos demonstrate setup and orientation only. They do not replace examination, current device instructions, contraindication screening, professional judgment, or individualized treatment planning.
The PT care model
The platform brings established physical-therapy decision points into a targeted facial and oral-motor workflow.
Connect history, systems review, movement observation, strength, endurance, coordination, and functional participation.
Use provider-selected isometric, isotonic, and controlled-speed resistance principles with clearly documented parameters.
Cue selective activation, reduce substitutions, and reinforce controlled movement strategies appropriate to the patient.
Establish a baseline, monitor immediate and delayed response, and modify loading as the patient advances.
Relate impairment-level work to expression, drinking, oral control, communication, and patient-centered participation goals.
Connect supervised visits with a provider-defined home program after safe and accurate technique is established.
Clinic onboarding
Account setup, organizational review, clinical training, workflow design, staff readiness, and a documented launch plan should precede routine use. The clinic should decide how referrals are screened, medical information is reviewed, goals and safety are documented, and inappropriate cases are redirected.

Program pathway
A deliberate implementation process supports consistent patient selection, staff performance, and quality review.
Assign a licensed clinician to oversee protocols, competency, documentation standards, escalation, and quality review.
Document inclusion, exclusion, referral, clearance, stopping, and reassessment criteria before launch.
Complete education in device use, fitting, sanitation, safety, measurement, and documentation before treating patients.
Set workflows for inventory, cleaning, scheduling, consent, account access, patient education, and follow-up.
Begin with a controlled cohort, review cases frequently, and correct workflow issues before expanding.
Monitor outcomes, adherence, incidents, documentation, referral experience, and patient feedback.
Referral ecosystem
Referral communication should accurately describe the functional problem, clinic capability, patient-selection process, and current regulatory status.
Describe a skilled rehabilitation pathway for selected patients with persistent facial weakness after stroke or other neurologic injury.
Coordinate around facial nerve conditions, post-procedural recovery, medical precautions, and timing of rehabilitation.
Provide a defined route for evaluation, functional goal setting, progressive care, and documented follow-up.
Coordinate when dentition, occlusion, oral tissue, jaw status, or procedural history affects candidacy or use.
Clarify PT and SLP roles when facial movement, oral control, communication, or swallowing needs overlap.
Use careful screening and accurate claims when facial muscle concerns arise in broader health or body-composition programs.
Clinic operations
The clinical service depends on repeatable operational controls as well as treatment skill.
Define responsibility for clinical oversight, scheduling, inventory, sanitation, purchasing, training records, and incident escalation.
Allow time for examination, fitting, instruction, treatment, documentation, cleaning, and planned reassessment.
Control device assignment, storage, cleaning, replacement, inspection, and removal of damaged components.
Provide clear setup, home-program, cleaning, storage, stopping-rule, and contact instructions.
Use approved systems and minimum-necessary information when coordinating professional care and program administration.
Document adverse responses, product concerns, corrective actions, retraining, and required reporting.
Documentation and payment
Coverage and payment depend on patient benefits, payer rules, contracts, diagnosis, skilled service, coding, documentation, and setting.
Confirm benefits, authorization requirements, referral rules, exclusions, and patient responsibility.
Connect examination findings, functional limitations, goals, clinical judgment, intervention details, response, and progression.
Select codes that accurately describe the skilled service provided rather than the device alone.
Maintain defensible records and respond to payer requests without overstating device status, evidence, or expected results.
Next step
Discuss clinical leadership, provider training, patient criteria, workflow, referral development, and a controlled launch plan.